
Autism is genetic. What does the science actually show?

It has taken me a minute to pull my thoughts together after what I think was a completely out-of-order announcement from the National Autistic Society.
On 15 September they told families that autism is genetic.
Not that genetics plays an important role in autism. Not that genetic variation can increase susceptibility. Not that autism is highly heritable.
Autism is genetic.
That is a very different statement.
They did not announce the discovery of an autism gene. They did not publish a new genomic study showing that inherited DNA explains autism in every autistic person. They reviewed the existing research and somehow moved from evidence about heritability, familial recurrence and genetic liability to a statement about cause.
And I think we need to be really clear about that distinction.
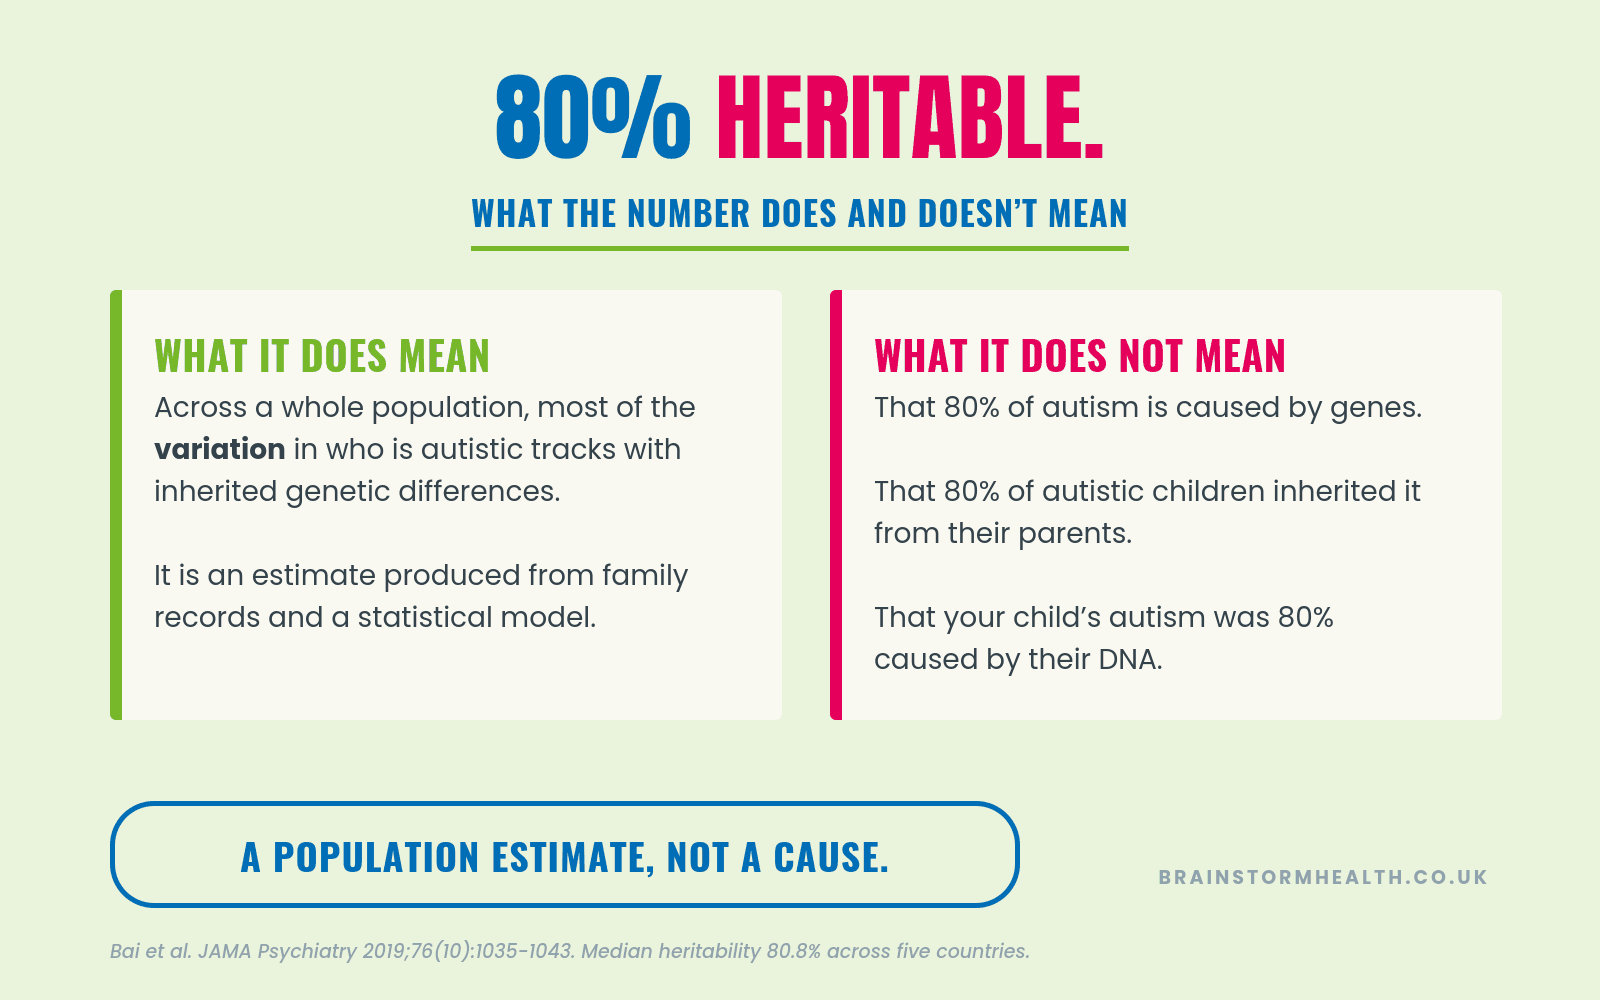
What does 80% heritable actually mean?
One of the studies most often quoted is Bai et al., published in JAMA Psychiatry in 2019.
More than two million children across five countries with a median autism heritability of 80.8%.
It is a huge study and 80.8% sounds incredibly convincing.
But what did they actually do?
They did not sequence the genomes of two million children and discover that 80% of autism was caused by inherited genes.
They used national population records and family relationships. Siblings, cousins and people related to different degrees. From those patterns they used statistical models to estimate how much of the variation in autism liability across the population could be attributed to inherited genetic effects and how much to other components.
That is valid genetic epidemiology.
But it is not the same thing as identifying the biological cause of autism in an individual child.
This is where the word heritability causes so much confusion.
Heritability is about why people in a population differ from each other.
It is not a pie chart of what caused a condition.
An 80% heritability estimate does not mean 80% of autism is genetic. It does not mean 80% of autistic people are autistic because of inherited genes. And it certainly does not mean that one child's autism was 80% caused by their DNA.
Even the Bai paper leaves gene-environment interaction and gene-environment correlation sitting there as important unanswered questions.
And that is a vastly important detail.
Because if your genes alter the way your immune system, placenta, mitochondria, folate metabolism or brain respond to the environment, where exactly does “genetic” stop and “environmental” begin?
The biology is unlikely to separate itself that neatly.
And even the 80% figure is not fixed
A large Swedish study published in 2014 estimated autism heritability at around 50%.
A later analysis of Swedish data, using different modelling assumptions, produced a figure around 83%.
Sweden did not suddenly acquire vastly more autism genes.
The modelling changed.
That does not make heritability useless. It tells us what it is: an estimate, dependent on the population being studied, the data available and the assumptions in the model.
That is very different from finding a mutation and demonstrating what it does biologically.
There is real genetic evidence. But that still does not get us to “autism is genetic”
There are autism studies that actually look at DNA.
Large genomic studies show that common inherited genetic variation contributes to autism susceptibility. Polygenic studies show that autism-associated variants are, on average, passed from parents to autistic children more often than expected.
There are also rare variants that can have much larger effects, including de novo mutations that arise in the child rather than being inherited from either parent.
A large 2022 sequencing study involving more than 63,000 people identified 72 genes at its strictest statistical threshold.
That is proper genetic evidence.
Genetics clearly matters.
In some children it may matter enormously.
But notice how different that statement is from saying that autism itself has now been shown to be caused by inherited genes.
Common variants can shift susceptibility. Rare variants can have large effects. New mutations can occur in the child. Different combinations can lead to very different outcomes.
None of that gives us one universal biological road into autism.
In fact, some of the newest genetics research is pointing in exactly the opposite direction.
A 2025 Nature Genetics study found different groups of autistic children with different patterns of common, inherited and de novo genetic variation.
Another major Nature paper that year found differences between earlier and later diagnosed autism, including different developmental trajectories and different polygenic profiles.
So even when we stay entirely inside the genetics, autism is splitting into different patterns.
That should make us more interested in heterogeneity, not less.
Then there is the question of prevalence
Autism was once considered very rare.
Victor Lotter's British study in the 1960s screened more than 76,000 children and identified what was then called autism in roughly 4.5 children per 10,000.
A modern study of more than seven million English schoolchildren found recorded autism prevalence of 1.76%, or 176 per 10,000.
You cannot simply put those two numbers next to each other and announce a forty-fold biological increase. Autism in 1966 was not being defined, recognised or diagnosed in anything like the way it is today.
Diagnostic criteria widened. Recognition improved. Girls were missed. Children without intellectual disability were missed. Diagnostic substitution happened. Services changed.
So we genuinely do not know how much of the rise in recorded autism represents a rise in the underlying biology.
But an 80% heritability estimate does not answer that question either.
And if even part of that increase is biological, ordinary inherited gene frequencies cannot change that dramatically in a couple of generations.
Myopia is a useful comparison here.
It is strongly heritable, yet rates have risen dramatically in some populations within a few generations.
The genes did not suddenly change.
The circumstances in which those genes were operating did.
Genetic susceptibility and environmental influence are not mutually exclusive. One can determine vulnerability while the other changes how often that vulnerability becomes expressed.
That is a much more interesting question to me than arguing about whether autism is “genetic” or “environmental”.
This is what we spend our days on at Brainstorm Health. Taking a proper history, and working out what else was going on for that particular child.
Book a free discovery callBecause there is a huge amount of biology still sitting on the table
This is the part of the NAS announcement I find hardest to understand.
By the end of 2010, researchers had already published hundreds of papers looking at immune dysregulation and inflammation in autism, mitochondrial dysfunction, oxidative stress and environmental exposures.
A broad review at the time identified 437 publications involving immune dysregulation or inflammation, 153 involving mitochondrial dysfunction, 115 involving oxidative stress and 190 involving environmental toxicant exposure.
That does not mean there were hundreds of papers proving these things cause autism.
There were not.
The studies varied enormously in quality and many were looking at association, not causation.
But these biological questions have been sitting there for decades.
And they have not gone away.

Some of that evidence is messy. Some of it is weak. Some findings will disappear as better studies are done.
Good.
That is how science is supposed to work.
But the answer to imperfect evidence is better research, not pretending the question has already been settled.
Maternal autoimmunity is a good example
A meta-analysis looking at maternal autoimmune disease included 9,775 autism cases and more than 950,000 controls.
Maternal autoimmune disease was associated with increased odds of autism in the child.
That does not tell us that maternal autoimmunity caused those children's autism. Shared genetics may be involved. Confounding may be involved. Different autoimmune diseases may carry different levels of association.
But it gives us something worth investigating.
Then there is the Finnish Prenatal Study of Autism, which I find particularly interesting because the blood was taken during pregnancy, years before anybody knew which children would later receive an autism diagnosis.
Researchers studied 967 matched mother-child pairs.
TPO antibodies were present in 6.15% of mothers whose children later developed childhood autism compared with 3.54% of controls.
The children of TPO-antibody-positive mothers had nearly 80% higher odds of childhood autism.
The maternal thyroid hormone concentrations themselves were not different between the groups.
That does not prove the antibodies caused autism.
But surely the next question is obvious.
What was that immune marker telling us about the pregnancy?
Why would we not want to understand it?
And then there are folate receptor antibodies
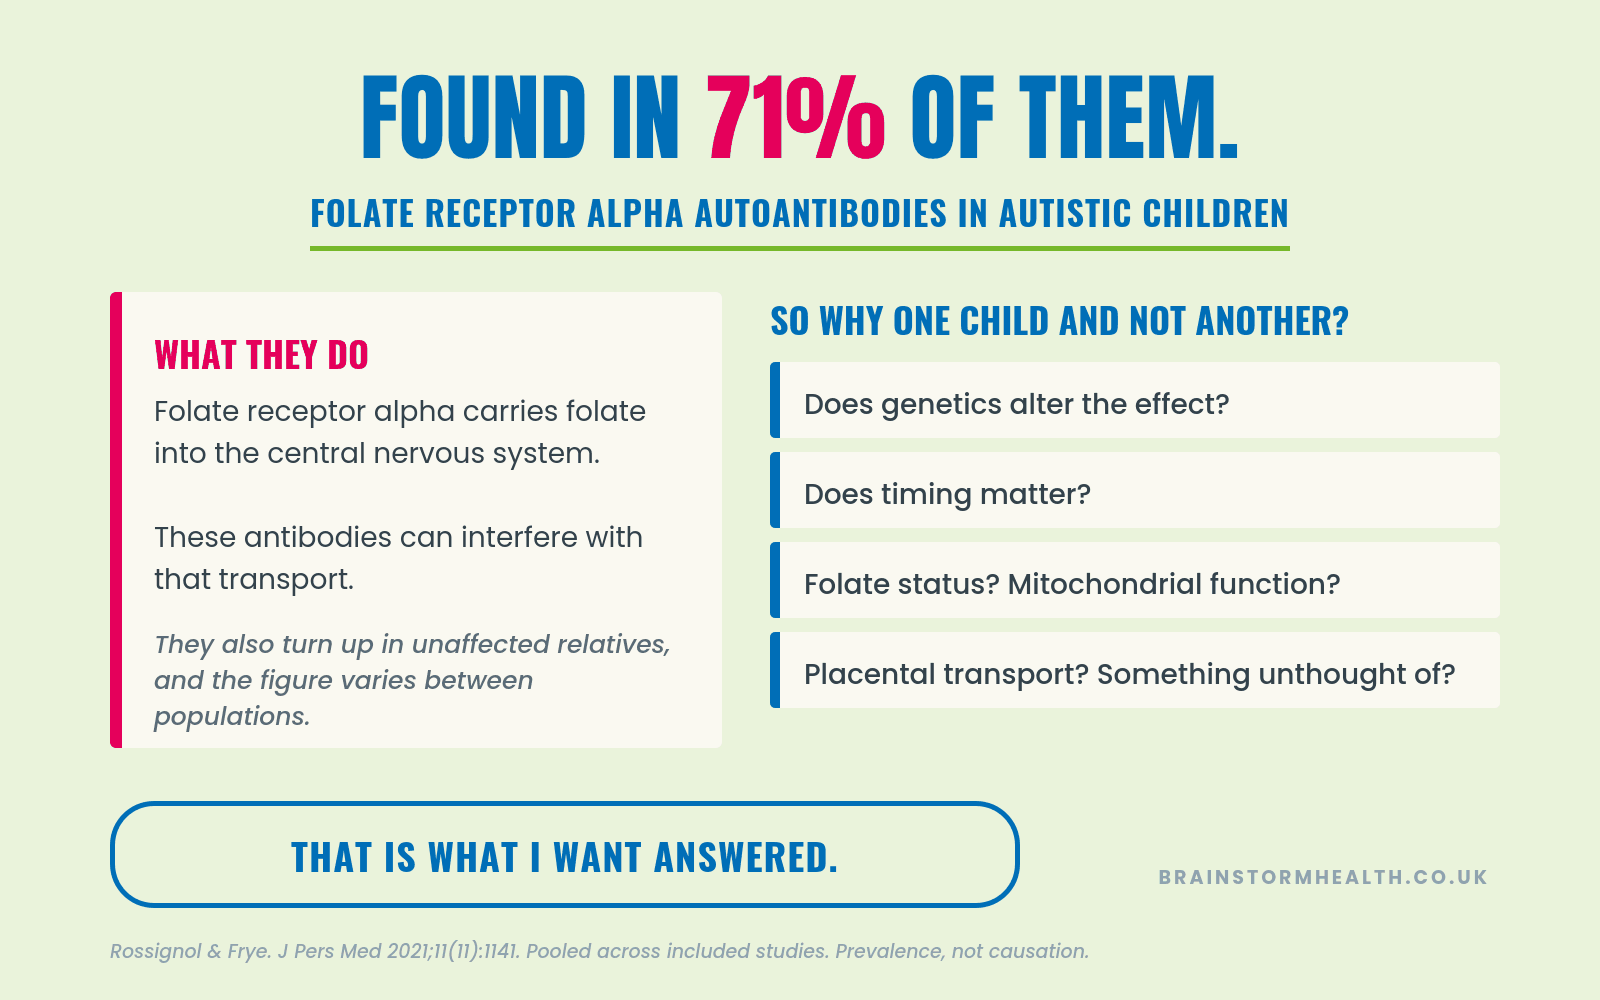
Folate receptor alpha helps transport folate into the central nervous system.
Autoantibodies against that receptor can interfere with that process.
A 2021 systematic review and meta-analysis reported folate receptor alpha autoantibodies in around 71% of autistic children across the studies included.
Seventy-one per cent.
Again, that does not mean folate receptor autoantibodies cause 71% of autism. They are also found in unaffected relatives and prevalence has varied considerably between populations.
But that is precisely why the biology is interesting.
Why does one antibody-positive child develop major developmental difficulties while another does not?
And then, almost unbelievably, the day after the NAS announcement came another paper
On 15 September NAS announced that autism is genetic.
On 16 September Science Advances published a study looking at maternal immune activation and what happened at the maternal-fetal interface.
It was a mouse study, so it cannot tell us what causes autism in human children.
But the biology it demonstrated is exactly why I think this conversation is nowhere near finished.
The pregnant mice received the same immune challenge.
The fetal outcomes were not the same.
Some were badly affected. Others were not.
The researchers found substantial changes in the placentas of the affected fetuses, involving inflammation, immune regulation and placental structure. IL-6 was important enough in this model that blocking it prevented the acute developmental abnormalities.
Forget autism for a moment.
The question is simply this:
Why did the same maternal immune event produce a different outcome in different foetuses?
And this is where genetics becomes really interesting to me, not as the whole answer, but as part of what determines why one foetus is vulnerable and another isn’t.
Genes and environment do not take turns
I think this is where the whole discussion has gone wrong for years.
Genes and environment are not two rival teams.
Genes build receptors, enzymes, immune pathways, mitochondrial machinery, nutrient transport systems, hormones, synapses and placental signalling.
So if a fetus carries a variant that changes the way the placenta responds to maternal inflammation, what caused the outcome?
The gene?
The inflammation?
The placenta?
The immune response?
Trying to pull those into separate boxes may completely miss the biology.
It may be the interaction itself that we should be studying.
Which brings me back to what NAS has actually said
Their current wording says:
“Most autistic people are autistic because of the genes they got from their parents.”
It says inherited genes determine “whether we are autistic or not”.
It says “other environmental factors cannot make a person autistic on their own”.
And it says “genetics is always involved alongside other environmental factors”.
Those are not simply statements that autism is highly heritable.
They are statements about cause.
And I do not think the evidence they reviewed allows that level of certainty.
A family study estimating heritability is not the same as identifying genes.
Finding common risk variants is not the same as showing those variants are sufficient to cause autism.
A polygenic score changes probability.
A rare pathogenic variant may be hugely important in one child and completely irrelevant to another child carrying the same diagnostic label.
And a de novo mutation, by definition, was not inherited from the parents in the first place.
The genetics tells us genetics matters.
It does not tell us the whole causal story has been solved.
Autism itself should stop us making statements like this
Autistic children are not one biological group.
Some show developmental differences from very early infancy.
Others develop apparently typically and then lose language, social engagement or other previously acquired skills.
Some have epilepsy.
Some have intellectual disability.
Some have severe gastrointestinal problems.
Some show immune abnormalities.
Some have mitochondrial dysfunction.
Some have a recognisable high-impact genetic condition.
Many do not.
And even the genetics is now starting to separate autism into different developmental and genetic patterns.
Maybe one of the biggest mistakes we have made is assuming that because children eventually arrive under the same diagnostic umbrella, they must all have travelled the same biological road to get there.
Why would we assume that?
This is why the wording matters
The National Autistic Society has enormous influence.
Parents will repeat this. Professionals will repeat it. Schools will repeat it. Journalists will repeat it.
And once “autism is genetic” becomes the accepted answer, all the other biological questions become that bit easier to brush aside.
What happened around a regression?
What was happening in the immune system?
What was happening during pregnancy?
What was the placenta doing?
Does cerebral folate transport matter in a subgroup?
Could mitochondrial vulnerability change the way a child responds to infection or inflammation?
Why can two children experience something similar and have completely different outcomes?
Researchers are still asking these questions because they have not been answered.
And I think we should be much further ahead with them than we are.
I don't want another theory
I am not interested in replacing “autism is genetic” with “autism is immune”.
Or mitochondrial.
Or environmental.
Or anything else.
That would just be the same mistake from the opposite direction.
I want to know what actually happened.
If a child's neurodevelopment was largely shaped by a high-impact genetic variant, follow that evidence.
If inherited susceptibility interacted with maternal immune activation, follow that.
If placental biology matters in a subgroup, follow it.
If cerebral folate transport is important in another, follow that.
If mitochondrial vulnerability changes the response to infection or inflammation, follow that too.
And if we eventually discover that there are several completely different biological roads leading to what we currently call autism, I would not find that surprising at all.
The research tells us that genetic variation contributes to autism susceptibility. In some people, individual genetic changes can have profound effects.
What it does not tell us is that we have solved the causal pathway for every autistic person.
We haven't.
And telling families that we have feels deeply wrong to me.
IMPORTANT
This information is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Always consult with medical doctors or qualified functional medicine practitioners before introducing any new supplement, test, or intervention.
If this has raised questions about your child, we'd love to help you find some answers.
REFERENCES
Bai D, Yip BHK, Windham GC, et al. (2019) Association of genetic and environmental factors with autism in a 5-country cohort. JAMA Psychiatry 76(10):1035-1043.
Visscher PM, Hill WG, Wray NR (2008) Heritability in the genomics era: concepts and misconceptions. Nature Reviews Genetics 9(4):255-266.
Sandin S, Lichtenstein P, Kuja-Halkola R, et al. (2014) The familial risk of autism. JAMA 311(17):1770-1777.
Sandin S, Lichtenstein P, Kuja-Halkola R, et al. (2017) The heritability of autism spectrum disorder. JAMA 318(12):1182-1184.
Gaugler T, Klei L, Sanders SJ, et al. (2014) Most genetic risk for autism resides with common variation. Nature Genetics 46(8):881-885.
Weiner DJ, Wigdor EM, Ripke S, et al. (2017) Polygenic transmission disequilibrium confirms that common and rare variation act additively to create risk for autism spectrum disorders. Nature Genetics 49(7):978-985.
Fu JM, Satterstrom FK, Peng M, et al. (2022) Rare coding variation provides insight into the genetic architecture and phenotypic context of autism. Nature Genetics 54(9):1320-1331.
Litman A, Sauerwald N, Green Snyder L, et al. (2025) Decomposition of phenotypic heterogeneity in autism reveals underlying genetic programs. Nature Genetics 57:1611-1619.
Zhang X, Grove J, Gu Y, et al. (2025) Polygenic and developmental profiles of autism differ by age at diagnosis. Nature 646:1146-1155.
Lotter V (1966) Epidemiology of autistic conditions in young children. Social Psychiatry 1:124-135.
Roman-Urrestarazu A, van Kessel R, Allison C, et al. (2021) Association of race/ethnicity and social disadvantage with autism prevalence in 7 million school children in England. JAMA Pediatrics 175(6):e210054.
Morgan IG, Ohno-Matsui K, Saw SM (2012) Myopia. The Lancet 379(9827):1739-1748.
Rossignol DA, Frye RE (2012) A review of research trends in physiological abnormalities in autism spectrum disorders: immune dysregulation, inflammation, oxidative stress, mitochondrial dysfunction and environmental toxicant exposures. Molecular Psychiatry 17(4):389-401.
Volk T, Lukito S, Radua J, et al. (2026) Atypical cytokine profiles in people on the autism spectrum: a comprehensive systematic review and meta-analysis including 54 cytokines. Molecular Psychiatry 31:5775-5786.
Frye RE, Rincon N, McCarty PJ, et al. (2024) Biomarkers of mitochondrial dysfunction in autism spectrum disorder: a systematic review and meta-analysis. Neurobiology of Disease 197:106520.
Zhu M, Yang H, Feng B, Jiang Y, Zhang Y (2026) Maternal pregnancy complications and offspring autism spectrum disorder risk: an umbrella review. Psychiatry Research 358:116987.
Chen SW, Zhong XS, Jiang LN, et al. (2016) Maternal autoimmune diseases and the risk of autism spectrum disorders in offspring: a systematic review and meta-analysis. Behavioural Brain Research 296:61-69.
Brown AS, Surcel HM, Hinkka-Yli-Salomäki S, et al. (2015) Maternal thyroid autoantibody and elevated risk of autism in a national birth cohort. Progress in Neuro-Psychopharmacology & Biological Psychiatry 57:86-92.
Rossignol DA, Frye RE (2021) Cerebral folate deficiency, folate receptor alpha autoantibodies and leucovorin (folinic acid) treatment in autism spectrum disorders: a systematic review and meta-analysis. Journal of Personalized Medicine 11(11):1141.
Sanchez-Martin I, Kukreja B, Henderson P, et al. (2026) Maternal-fetal immune conflict contributes to male-specific impairments in a mouse model of neurodevelopmental disorders. Science Advances 12(38):eaeg0779.